Home » Posts tagged 'CANCER' (Page 13)
Tag Archives: CANCER
 DRUG APPROVALS BY DR ANTHONY MELVIN CRASTO
.....FOR BLOG HOME CLICK HERE
Flag and hits
ORGANIC SPECTROSCOPY

SUBSCRIBE

 Subscribe in a reader
Enter your email address:
Delivered by FeedBurner
Subscribe to New Drug Approvals by Email


Kyowa Hakko Kirin Korea begins patient recruitment in phase I/II study of BIW-8962 in lung cancer
Kyowa Hakko Kirin Korea begins patient recruitment in phase I/II study of BIW-8962 in lung cancer
http://www.kyowa-kirin.com/news_releases/2011/pdf/e20110802_04.pdf
http://clinicaltrials.gov/ct2/show/NCT01898156
Kyowa Hakko Kirin Korea Co., Ltd
This Phase 1/2 study is designed to assess the following: safety and tolerability of BIW-8962, Dose Limiting Toxicities (DLTs), Maximum Tolerated Dose (MTD), Recommended Phase 2 Dose (RP2D) in Phase 1 and preliminary efficacy in Phase 2 in subjects with advanced/recurrent lung cancer or mesothelioma.
http://www.myeloma.org.uk/patient-information/drug-development/hcp-drug-scanner/biw-8962/
Compound Suffocates Tumors
Scientists have discovered a new molecule that prevents cancer cells from responding and surviving when starved of oxygen and which could be developed into new treatments for the disease, according to new research published in the Journal of the American Chemical Society.
Cancer Research UK scientists at the University of Southampton found that this molecule targets the master switch—HIF-1—that cancer cells use to adapt to low oxygen levels, a common feature in the disease.
read all at
Find out more:
- Cancer Sciences Unit
- Is it your ambition to help cure cancer? If so, visit: www.southampton.ac.uk/medicine/undergraduate/index.page
Curis phase 1 Cancer Trial for CUDC-427 Begins

CUDC-427, GDC-0917; RG-7459
Genentech Inc (Roche Holding AG)
Curis licenses GDC-0917 from Genentech
Curis Cancer Trial Begins
Curis Inc. has initiated patient dosing in a second Phase 1 dose-escalation study of CUDC-427 that is being conducted using a continuous, twice-daily oral dosing regimen in patients with advanced and refractory solid tumors or lymphoma.
FULL STORY
About CUDC-427 (GDC-0917)
CUDC-427 is an orally bioavailable small molecule that is designed to promote cancer cell death by antagonizing IAP proteins. IAP proteins are a family of functionally and structurally related proteins that promote cancer cell survival by inhibiting programmed cell death, also known as apoptosis, which is a normal process inherent in every cell. Using IAP proteins and other anti-apoptotic factors, cancer cells evade apoptosis in response to a variety of signals, including those provided by anti-cancer agents such as chemotherapy, or naturally occurring inflammatory and immune signals transmitted through members of the tumor necrosis factor, or TNF, family of factors. Evasion from apoptosis is a fundamental mechanism whereby human cancers develop resistance to standard anti-cancer treatments. IAP inhibitors such as CUDC-427 are designed to counteract the effects of IAP proteins, thus shifting the balance away from cancer cell survival and allowing apoptosis to proceed.
CUDC-427 was designed to mimic the endogenous IAP antagonist mitochondrial protein second mitochondria-derived activator of caspases/direct IAP-binding protein (Smac/DIABLO) that is released into the cytoplasm in response to pro-apoptotic stimuli. CUDC-427 has demonstrated single-agent and combination anti-tumor activity in mouse xenograft tumor models when administered orally on a daily schedule, and IND-enabling safety studies have shown it to be well tolerated when dosed daily by oral administration, potentially enabling sustained target inhibition.
In October 2010, an open-labeled, uncontrolled, dose-escalation, Phase I clinical trial of CUDC-427 (NCT01226277; IAM4914g) began in patients with refractory solid tumors or lymphoma. Genentech recently completed this Phase I clinical trial in which 42 people received daily oral doses of CUDC-427 for two weeks, followed by a one week rest period. This 21-day cycle is repeated until disease progression or study discontinuation for any other reason. The primary endpoints of the study include evaluating the safety and tolerability and the pharmacokinetics of CUDC-427 in people with solid tumors or lymphoma and determining the maximum-tolerated-dose and a potential recommended dose for further clinical studies. Secondary endpoints include a preliminary assessment of anti-tumor activity of CUDC-427 and evaluating pharmacodynamic markers. Genentech plans to present full study results at a medical conference in mid-2013. Please refer to http://www.clinicaltrials.gov for additional study details.
About Inhibitor of Apoptosis Proteins
Impairment of programmed cell death or apoptosis often contributes to the formation and progression of cancer, and evasion of apoptosis is one of the primary strategies by which cancer cells develop resistance to anticancer therapies. Inhibitor of apoptosis (IAP) proteins are a family of functionally and structurally related proteins which include X-linked IAP (XIAP), cellular IAPs (cIAP1 and cIAP2), and melanoma IAP (ML-IAP). They confer protection from death-inducing stimuli by exerting a range of biological activities that promote cancer cell survival and proliferation. Some even directly inhibit caspases, critical players in the execution of apoptosis.
Mutations, amplifications and chromosomal translocations of IAP genes are associated with various solid and hematologic cancer types, and increased IAP expression has been associated with an unfavorable prognosis and poor outcome for patients. As a consequence, IAP proteins are considered promising molecular targets for anticancer therapy.
Antibody Effective Against Norovirus

Antibody Effective Against Norovirus
Researchers have released data showing that a monoclonal antibody can neutralize human norovirus. Norovirus causes roughly 20 million cases of acute diarrhea and vomiting annually in the United States, alone. It is also responsible for roughly 800 deaths annually.
FULL STORY
What is Norovirus?

Norovirus is a stomach bug that sets in within 10 hours of transmission and usually lasts up to three days. It is completely different from the flu in that only your stomach is affected. While most people recover completely after three days, norovirus is more serious for young children, the elderly and people with other serious health conditions. Every year 70,000 people are hospitalized and 800 deaths are caused by the virus.
What are the symptoms?
The most common symptoms of norovirus include stomach pain, vomiting, diarrhea and nausea. Some people also experience a low-grade fever, headache and body ache. Because it is common to have continued vomiting and diarrhea during the three days of illness, dehydration is another concern for those affected.
How do you get it?
Norovirus is spread through direct contact with an infected person’s vomit or feces. Most commonly, unwashed hands can be attributed to spreading the virus through surfaces or food. The virus spreads quickly in enclosed spaces like cruise ships, nursing homes and schools.
What is the treatment?
Unfortunately, there are no medications to treat norovirus. Health care providers say the best thing to do is try to stay hydrated, rest and wait for the virus to run its course. People who are unable to keep fluids down may need to receive fluids intravenously.
How can you protect yourself?
Hand washing is the best defense against the norovirus, since no one is immune to the always-changing strains of the virus. However, new research has found hand sanitizers are not affective in killing the virus. Avoid direct contact with anyone who is infected and pay close attention to cleaning and preparing food. Also, anyone who is infected should not prepare food. Use disinfectants to wipe down all surfaces that have come in contact with someone who is infected. Also, launder infected clothes immediately on the longest wash cycle to help from spreading the virus.
Biosimilars applications under review by EMA – 2013 Q2

The European Medicines Agency (EMA) is the body responsible for approval of biosimilars within the EU. A legal framework for approving biosimilars was established in 2003. Approval of biosimilars is based on an abbreviated registration process, which allows biosimilars manufacturers to provide a reduced package of information compared to originator drugs, provided they can prove ‘similarity’ to the originator or ‘reference drug’.
read all at
http://www.gabionline.net/Biosimilars/General/Biosimilars-applications-under-review-by-EMA-2013-Q2
First biosimilar filgrastims launched in Japan


International nonproprietary name: Filgrastim
Chemical name: N-L- Methionyl colony-stimulating factor (human genetically engineered); non-glycated protein consisted of 175 amino acids.
Chemical name: N-L- Methionyl colony-stimulating factor (human genetically engineered); non-glycated protein consisted of 175 amino acids.
Filgrastim is a granulocyte colony-stimulating factor (G-CSF) analog used to stimulate the proliferation and differentiation of granulocytes.[1] It is produced by recombinant DNA technology. The gene for human granulocyte colony-stimulating factor is inserted into the genetic material of Escherichia coli. The G-CSF then produced by E. coli is different from G-CSF naturally made in humans.

Hematopoietic growth factor. Interacting with receptors on the surface of hematopoietic cells it regulates production and release of neutrophils from the bone marrow to the peripheral blood. Dose dependant number growth of neutrophils with normal or increased functional activity is passing for 24 hours.
Filgrastim is marketed under several brand names, including Neupogen (Amgen), Imumax(Abbott Laboratories), Grafeel (Dr. Reddy’s Laboratories), Neukine (Intas Biopharmaceuticals), Emgrast (Emcure Pharmaceuticals), Religrast (Reliance Life Sciences), Zarzio (Sandoz), Nufil (Biocon) and others.
Apricus Biosciences is currently developing and testing a product under the brand nameNupen which can deliver filgrastim through the skin to improve post-chemotherapy recovery of neutrophil counts.
Filgrastim is also used to increase the number of hematopoietic stem cells in the blood before collection by leukapheresis for use in hematopoietic stem cell transplantation.Filgrastim is used to treat neutropenia,[2] stimulating the bone marrow to increase production of neutrophils. Causes of neutropenia include chemotherapy and bone marrow transplantation.
Filgrastim should not be used in patients with known hypersensitivity to E. coli-derived proteins.
The most commonly observed adverse effect is mild-to-moderate bone pain after repeated administration and local skin reactions at the site of injection.[3] Other observed adverse effects include serious allergic reactions (including a rash over the whole body, shortness of breath, wheezing, dizziness, swelling around the mouth or eyes, fast pulse, and sweating), ruptured spleen (sometimes resulting in death), alveolar hemorrhage, acute respiratory distress syndrome, and hemoptysis.[3] Severe sickle cell crises, in some cases resulting in death, have been associated with the use of filgrastim in patients with sickle cell disorders.[4]
Drug interactions between filgrastim and other drugs have not been fully evaluated. Drugs which may potentiate the release of neutrophils‚ such as lithium‚ should be used with caution.
Increased hematopoietic activity of the bone marrow in response to growth factor therapy has been associated with transient positive bone imaging changes; this should be considered when interpreting bone-imaging results.[5]
Filgrastim has not been studied in pregnant women and its effects on unborn babies is unknown. If taking filgrastim while pregnant, it is possible that traces of the drug could be found in the baby’s blood. It is not known if the drug can get into human breast milk.
- Beveridge, R. A.; Miller, J. A.; Kales, A. N.; Binder, R. A.; Robert, N. J.; Harvey, J. H.; Windsor, K.; Gore, I. et al. (1998). “A Comparison of Efficacy of Sargramostim (Yeast-Derived RhuGM-CSF) and Filgrastim (Bacteria-Derived RhuG-CSF) in the Therapeutic Setting of Chemotherapy-Induced Myelosuppression”. Cancer Investigation 16 (6): 366–373. doi:10.3109/07357909809115775.PMID 9679526. edit
- Crawford, J.; Glaspy, J. A.; Stoller, R. G.; Tomita, D. K.; Vincent, M. E.; McGuire, B. W.; Ozer, H. (2005). “Final Results of a Placebo-Controlled Study of Filgrastim in Small-Cell Lung Cancer: Exploration of Risk Factors for Febrile Neutropenia”. Supportive Cancer Therapy 3 (1): 36–46. doi:10.3816/SCT.2005.n.023. PMID 18632435. edit
- Neupogen “Neupogen: Patient Information Leaflet”. Amgen. Retrieved 24 June 2013.
- “NEUPOGEN® Patient Guide”. Amgen. Retrieved 24 June 2013.
- “Neupogen”. RxList. 4 June 2012. Retrieved 23 June 2013.
- Budiono Santoso; Chris J. van Boxtel; Boxtel, Christoffel Jos van (2001). Drug benefits and risks: international textbook of clinical pharmacology. New York: Wiley. ISBN 0-471-89927-5.
- “Neupogen information”. Retrieved 20 October 2005.
Alkermes unveils three new drug candidates

Alkermes has unveiled three new drug candidates, including: a monomethyl fumarate (MMF) prodrug programme for the treatment of multiple sclerosis; ALKS 7106 for the treatment of pain; and RDB 1419, a cancer immunotherapy candidate based on interleukin-2 (IL-2) and its receptors, Alkermes’ first proprietary biologic.
According to Alkermes, these drug candidates demonstrate the company’s focus on unmet medical needs in specific patient populations and show the productivity of its expanded R&D capabilities.
read all at
http://www.manufacturingchemist.com/news/article_
page/Alkermes_unveils_three_new_drug_candidates/90167

The clinical benefit of high-dose toremifene for metastatic breast cancer

http://www.ncbi.nlm.nih.gov/pubmed/23863727
Source
Dept. of Surgery, Saga University Faculty of Medicine.
Abstract
Introduction: Toremifene(TOR)is a selective estrogen receptor modulator(SERM). A high dose of 120 mg TOR(HD-TOR) has been used for recurrent breast cancer in Japan, but there is still insufficient evidence regarding the efficacy of HD-TOR. Patients and methods: HD-TOR was administered for recurrent or metastatic breast cancer between January 2003 and May 2012. The primary end point of the study was the tumor response rate. Bone metastasis cases were excluded from the efficacy analysis, but were included in the safety population. Results: A total of 21 patients registered in the study and the 2 patients with bone metastasis only were excluded from the efficacy analysis. The median follow-up period was 8. 3 months. None of the patients in the study had a CR, 4 had a PR(21. 1%), 9 had SD(47. 4%), and 6 had PD(31. 6%). Eight of the 9 SD cases had a long-term SD. The ORR was 21. 1% and the CB rate was 63. 2%. The median TTP of CB cases was 18. 3 months. None of the patients discontinued treatment because of a grade 3 or grade 4 adverse effects. Conclusion: In summary, the current study showed that HD-TOR may lead to a CB for recurrent breast cancer in first- or second-line treatment rather than thirdline. In particular, HD-TOR may give a benefit in highly endocrine-sensitive cases.

toremifene
Toremifene citrate is an oral selective estrogen receptor modulator (SERM) which helps oppose the actions of estrogen in the body. Licensed in the United States under the brand name Fareston, toremifene citrate is FDA-approved for use in advanced (metastatic)breast cancer. It is also being evaluated for prevention of prostate cancer under the brand name Acapodene.[1]
In 2007 the pharmaceutical company GTx, Inc was conducting two different phase 3clinical trials; First, a pivotal Phase clinical trial for the treatment of serious side effects ofandrogen deprivation therapy (ADT) (especially vertebral/spine fractures and hot flashes, lipid profile, and gynecomastia) for advanced prostate cancer, and second, a pivotal Phase III clinical trial for the prevention of prostate cancer in high risk men with high gradeprostatic intraepithelial neoplasia, or PIN. Results of these trials are expected by first quarter of 2008[2]
An NDA for the first application (relief of prostate cancer ADT side effects) was submitted in Feb 2009,[3] and in Oct 2009 the FDA said they would need more clinical data, e.g. another phase III trial.[4]
- Price N, Sartor O, Hutson T, Mariani S. Role of 5a-reductase inhibitors and selective estrogen receptor modulators as potential chemopreventive agents for prostate cancer.Clin Prostate Cancer 2005;3:211-4. PMID 15882476
- “GTx’s Phase III Clinical Development of ACAPODENE on Course Following Planned Safety Review” (Press release). GTx Inc. 2007-07-12. Retrieved 2006-07-14.
- “GTx Announces Toremifene 80 mg NDA Accepted for Review by FDA” (Press release).
- “GTx and Ipsen End Prostate Cancer Collaboration due to Costs of FDA-Requested Phase III Study”. 2 Mar 2011.

Breast Cancer Drugs in Late-Stage Development/Recently Approved
The article is 2012-2013 based and reader discretion is sought to ascertian the stage of approval

Afinitor® (everolimus)
https://newdrugapprovals.wordpress.com/2013/04/27/drug-spotlight-afinitor-everolimus-novartis/
Sponsor: Novartis
Method of Action: Mammalian target of rapamycin (mTOR) inhibitor
Indications/Phase of Trial: Hepatocellular carcinoma; human epidermal growth factor receptor 2-positive (HER2+) breast cancer first-line and second-line; lymphoma; nonfunctional carcinoid tumor (Phase III; all new indications)
Approved in July in U.S., EU for advanced hormone-receptor-positive (HR+) and human epidermal growth factor Receptor 2-negative (HER2-) metastatic breast cancer with exemestane in postmenopausal women who have already received certain other medicines for their cancer
Approved earlier for adults with pancreatic neuroendocrine tumors (PNET) that cannot be treated with surgery; adults with advanced renal cell carcinoma (RCC) when certain other medicines have not worked; adults with angiomyolipoma, seen with tuberous sclerosis complex (TSC), when surgery is not required immediately; and adults and children with TSC who have a brain tumor called subependymal giant cell astrocytoma (SEGA) that cannot be removed completely by surgery
Avastin (Bevacizumab; RG435)
Sponsor: Roche/Genentech
Method of Action: Monoclonal antibody; Vascular endothelial growth factor (VEGF) inhibitor
Indications/Phase of Trial: U.S.: Relapsed ovarian cancer, platinum-sensitive (Registration); first-line metastatic breast cancer and first-line metastatic ovarian cancer (both Phase III).
EU: Relapsed platinum-resistance ovarian cancer (Phase III)
Metastatic colorectal cancer, treatment beyond progression (Registration); adjuvant breast cancer, HER2- and HER2+; adjuvant NSCLC; first-line glioblastoma (GBM) multiforme; high-risk carcinoid (all Phase III)
Approved for metastatic colorectal cancer (mCRC) when started with the first or second intravenous 5-FU–based chemotherapy for metastatic cancer; advanced nonsquamous non-small-cell lung cancer (NSCLC) with carboplatin and paclitaxel in people who have not received chemotherapy for their advanced disease; metastatic RCC (mRCC) with interferon alfa; and GBM in adult patients whose cancer has progressed after prior treatment. Effectiveness based on tumor response, as no data have shown whether Avastin improves disease-related symptoms or survival in people previously treated for GBM
Approval conditionally granted in 2008 and withdrawn November 2011 for HER2- metastatic breast cancer (mBC) with Paclitaxel

Buparlisib (BKM120)
Sponsor: Novartis
Method of Action: Pan-PI3K inhibitor
Indications/Phase of Trial: mBC (Phase III and confirmatory Phase I/II); with Fulvestrant, in postmenopausal women with hormone receptor-positive HER2- locally advanced or mBC which progressed on or after aromatase inhibitor (AI) treatment (Phase III; BELLE-2 study recruiting as of November 2012); with Fulvestrant, in postmenopausal women with hormone receptor-positive HER2- AI-treated, locally-advanced or mBC who progressed on or after mTOR inhibitor-based treatment (Phase III; BELLE-3 study, recruiting as of October 2012); with Paclitaxel in patients with HER2- inoperable locally advanced or mBC, with or without PI3K pathway activation (Phase III; BELLE-4 study, recruiting as of November); metastatic castration-resistant prostate cancer (CRPC; Phase II; recruiting as of October); recurrent glioblastoma (Phase II; recruiting as of November); recurrent/metastatic head and neck squamous cell carcinoma (Phase II; recruiting as of October); endometrial cancer (Phase I/II); NSCLC (Phase I/II); prostate cancer (Phase I/II); GBM multiforme (Phase I/II); with Fulvestrant in postmenopausal women with estrogen receptor-positive metastatic breast cancer (Phase I); previously treated advanced colorectal cancer (Phase I)

Faslodex (Fulvestrant Injection)
Sponsor: AstraZeneca
Method of Action: Estrogen receptor antagonist
Indications/Phase of Trial: First line HR+ mBC (Phase III; FALCON study commenced Oct. 29)
Approved for HR+ mBC in women who have experienced menopause and whose breast cancer has worsened after they were treated with antiestrogen medications

Herceptin (Trastuzumab; RG597)
Sponsor: Roche, in partnership with Halozyme
Method of Action: Humanized monoclonal antibody designed to target and block the function of HER2+
Indications/Phase of Trial: EU: Early HER2+ breast cancer, subcutaneous formulation (Registration)
Approved for early-stage HER2+ breast cancer that has spread into the lymph nodes, and HER2+ breast cancer that has not spread into the lymph nodes and is estrogen receptor/progesterone receptor-negative (ER-/PR-) or have one high-risk feature. High-risk is defined as estrogen receptor/progesterone receptor-positive (ER+/PR+) with one of the following features: tumor size >2 cm, age <35 years, or tumor grade 2 or 3. Can be used with Adriamycin® (doxorubicin), Cytoxan® (cyclophosphamide), and either Taxol® (paclitaxel) or Taxotere® (docetaxel); or with Taxotere and Paraplatin® (carboplatin); or alone after treatment with multiple other therapies, including an anthracycline (Adriamycin)-based chemotherapy
Also approved alone for the treatment of HER2+ breast cancer in patients who have received one or more chemotherapy courses for metastatic disease; and with paclitaxel for first-line treatment of HER2+ mBC

Iniparib (Tivolza; BSI-201; SAR240550)
Sponsor: Sanofi, through acquisition of original developer BiPar Sciences
Method of Action: Poly (ADP-ribose) polymerase 1 (PARP1) inhibitor
Indications/Phase of Trial: Stage IV squamous NSCLC (Phase III; NME); solid tumors such as sarcoma and breast, uterine, lung, and ovarian cancers (Phase I/II)
Phase III trial in breast cancer failed January 2011 by failing to improve survival and progression-free survival (PFS) in breast cancer patients

Nexavar® (Sorafenib)
https://newdrugapprovals.wordpress.com/2013/07/16/nexavar-sorafenib/
Sponsor: Onyx Pharmaceuticals
Method of Action: Dual-action inhibitor that targets RAF/MEK/ERK pathway in tumor cells and tyrosine kinases
Indications/Phase of Trial: Liver cancer adjuvant (Phase III; STORM study); kidney cancer adjuvant (Phase III; SORCE/ASSURE study); thyroid cancer monotherapy (Phase III; DECISION study); breast cancer with capecitabine (Phase III; RESILIENCE study)
Approved for hepatocellular carcinoma (HCC) and RCC

Perjeta (Pertuzumab; RG1273)
Sponsor: Roche/Genentech
Method of Action: HER2/neu receptor antagonist
Indications/Phase of Trial: EU: With Herceptin and docetaxel chemotherapy for previously-untreated HER2+ mBC or locally recurrent, inoperable breast cancer in patients who have not received previous treatment or whose disease has returned after treatment in the early-stage setting (Registration)
U.S.: Approved June 2012 for HER2+ mBC with Herceptin (trastuzumab) and docetaxel, in patients who have not received prior anti-HER2 therapy or chemotherapy for metastatic disease
Switzerland: Approved August 2012 for HER2+ breast cancer with Herceptin (trastuzumab) and docetaxel in patients with advanced or locally recurring breast cancer that has not previously been treated with chemotherapy

Ridaforolimus (MK-8669; AP23573; formerly Deforolimus)
Sponsor: Merck, under exclusive worldwide license agreement with Ariad Pharmaceuticals
Method of Action: Oral inhibitor of mammalian target of rapamycin inhibitor (mTOR)
Indications/Phase of Trial: Maintenance therapy for metastatic soft-tissue sarcoma and bone sarcomas after at least four chemotherapy cycles (under review after receiving Complete Response letter from FDA in June; NME); breast cancer with exemestane, compared to breast cancer with dalotuzumab and exemestane (Phase II; recruiting as of November); advanced head and neck cancer, NSCLC and colon cancer, with cetuximab (Phase II); pediatric patients with advanced solid tumors (Phase I; recruiting as of September); with dalotuzumab in pediatric patients with advanced solid tumors (Phase I; recruiting as of August); advanced RCC, with vorinostat (Phase I; recruiting as of October 2012); breast cancer, with dalotuzumab (Phase I: recruiting as of September); endometrial and ovarian cancers, with paclitaxel and carboplatin (Phase I; recruiting as of September 2012); advanced cancer, with MK-2206 and MK-0752 (Phase I: recruiting as of September 2012); advanced cancer, with dalotuzumab, MK-2206 and MK-0752 (Phase I: recruiting as of August 2012)
Tivozanib (ASP4130; AV-951)
Sponsor: Aveo Oncology and Astellas
Method of Action: Tyrosine kinase inhibitor; inhibits VEGF receptor 1, 2, and 3
Indications/Phase of Trial: U.S.: Advanced RCC (Registration; NDA filed September 2012); tivozanib biomarkers in solid tumors (Phase II; BATON study); stage IV metastatic colorectal cancer (mCRC), with mFOLFOX6, and compared with bevacizumab and mFOLFOX6 (Phase II; recruiting as of November); additional data as first-line therapy for advanced RCC, followed by sunitinib (Phase II; TAURUS study, enrollment initiated in October 2012); advanced solid tumors, with capecitabine (Xeloda®; Phase I; recruiting as of October)
EU: Advanced RCC (Phase III)
Trastuzumab-DM1 (T-DM1; Trastuzumab emtansine; RG3502)
Sponsor: Roche, with linker technology developed by ImmunoGen
Method of Action: Antibody-drug conjugate, consisting of the antibody trastuzumab and the chemotherapy DM1 attached via a stable linker
Indications/Phase of Trial: U.S.: HER2+, unresectable locally-advanced or mBC who have received prior treatment with Herceptin (trastuzumab) and a taxane chemotherapy (Registration; Priority review approved Nov. 7; action date Feb. 26, 2013)
EU: Marketing Authorization Application for HER2+ mBC accepted for review by European Medicines Agency

Tyverb/Tykerb (lapatinib)
Sponsor: GlaxoSmithKline
Method of Action: Human epidermal growth factor receptor-2 (Her2) and epidermal growth factor receptor (EGFR) dual kinase inhibitor
Indications/Phase of Trial: mBC with trastuzumab (Registration); breast cancer, adjuvant therapy (Phase III); Gastric cancer (Phase III); head & neck squamous cell carcinoma, resectable disease (Phase III)
Xgeva (denosumab)
Sponsor: Amgen, with commercialization by GlaxoSmithKline in countries where Amgen has no presence
Method of Action: Fully human monoclonal antibody that specifically targets a ligand known as RANKL that binds to a receptor known as RANK
Indications/Phase of Trial: Delay or prevention of bone metastases in breast cancer (Phase III); delay or prevention of bone metastases in prostate cancer (Phase III)
Approved for prevention of fractures in men with advanced prostate cancer
Rejected in April for supplemental Biologics License Application to treat men with CRPC at high risk of developing bone metastases

Yondelis® (trabectedin)
Sponsor: Johnson & Johnson; developed in collaboration with PharmaMar
Method of Action: Binds to minor groove of DNA, interfering with the cell division and gene transcription processes, as well as DNA’s repair machinery
Indications/Phase of Trial: U.S.: Locally advanced or metastatic soft tissue sarcoma excluding leiomyosarcoma and liposarcoma who have relapsed or are refractory to standard-of-care treatment (Phase III; recruiting as of November); soft tissue sarcoma, excluding liposarcoma and leiomyosarcoma (L-type sarcoma), in previously-treated patients who cannot be expected to benefit from currently available therapeutic options (Phase III; recruiting as of November); locally advanced or metastatic L-sarcoma (liposarcoma or leiomyosarcoma) who were previously treated with at least an anthracycline and ifosfamide-containing regimen, or an anthracycline-containing regimen and one additional cytotoxic chemotherapy regimen, compared with dacarbazine group (Phase III; recruiting as of November); breast cancer and pediatric tumors (Phase II); Advanced malignancies and liver dysfunction (Phase I; recruiting as of November)
EU: Approved for advanced or metastatic soft tissue sarcoma, and for relapsed platinum-sensitive ovarian cancer, with DOXIL®/Caelyx®

Xtandi® Capsules (Enzalutamide; formerly MDV3100)
Sponsor: Medivation in collaboration with Astellas
Method of Action: Androgen receptor inhibitor
Indications/Phase of Trial: Prechemotherapy CRPC in patients who have failed luteinizing hormone-releasing hormone (LHRH) analog treatment only, as well as patients who have failed both LHRH analog and anti-androgen treatment. (Phase III; PREVAIL study); prostate cancer neoadjuvant therapy (Phase II); prechemo metastatic prostate cancer in Europe (Phase II; TERRAIN); prechemo metastatic and nonmetastatic prostate cancer patients in U.S. (Phase II; STRIVE); prostate cancer Hormone-naïve (Phase II; ASPIRE); prostate cancer with docetaxel (Phase I); breast cancer (Phase I)
EU: Marketing Authorization Application submitted June 2012 to European Medicines Agency, for patients with metastatic CRPC who have received docetaxel-based chemotherapy
Japan: Metastatic CRPC who have received docetaxel-based chemotherapy (Phase II)
Approved Aug. 31 for patients with metastatic CRPC who have previously received docetaxel. As a post-marketing requirement, Medivation and Astellas agreed to conduct an open-label safety study of Xtandi (160 mg/day) in patients at high risk for seizure, with data to be submitted to FDA in 2019
UK launch for Astellas’ prostate cancer drug
http://www.pharmatimes.com/Article/13-07-19/UK_launch_for_Astellas_prostate_cancer_drug.aspx
UK patients with advanced prostate cancer have been given access to a new treatment that could prolong survival following the launch of Astella’s Xtandi in the country.
Xtandi (enzalutamide) was licensed in Europe this month for the treatment of men with advanced prostate cancer whose disease has become resistant to first-line hormonal treatments and has progressed following docetaxel chemotherapy.
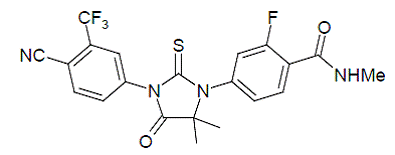
Enzalutamide is an androgen receptor inhibitor. The chemical name is 4-{3-[4-cyano-3-(trifluoromethyl)phenyl]-5,5dimethyl-4-oxo-2-sulfanylideneimidazolidin-1-yl}-2-fluoro-N-methylbenzamide.
The molecular weight is 464.44 and molecular formula is C21H16F4N4O2S. The structural formula is:
 |
Enzalutamide is a white crystalline non-hygroscopic solid. It is practically insoluble in water.
XTANDI is provided as liquid-filled soft gelatin capsules for oral administration. Each capsule contains 40 mg of enzalutamide as a solution in caprylocaproyl polyoxylglycerides. The inactive ingredients are caprylocaproyl polyoxylglycerides, butylated hydroxyanisole, butylated hydroxytoluene, gelatin, sorbitol sorbitan solution, glycerin, purified water, titanium dioxide, and black iron oxide.


