New Drug Approvals

Home » Uncategorized (Page 126)

Category Archives: Uncategorized

DRUG APPROVALS BY DR ANTHONY MELVIN CRASTO .....FOR BLOG HOME CLICK HERE

Blog Stats

  • 5,102,139 hits

Flag and hits

Flag Counter

Enter your email address to follow this blog and receive notifications of new posts by email.

Join 37.7K other subscribers
Follow New Drug Approvals on WordPress.com

Archives

Categories

Recent Posts

Flag Counter

ORGANIC SPECTROSCOPY

Read all about Organic Spectroscopy on ORGANIC SPECTROSCOPY INTERNATIONAL 

Enter your email address to follow this blog and receive notifications of new posts by email.

Join 37.7K other subscribers
DR ANTHONY MELVIN CRASTO Ph.D

DR ANTHONY MELVIN CRASTO Ph.D

DR ANTHONY MELVIN CRASTO, Born in Mumbai in 1964 and graduated from Mumbai University, Completed his Ph.D from ICT, 1991,Matunga, Mumbai, India, in Organic Chemistry, The thesis topic was Synthesis of Novel Pyrethroid Analogues, Currently he is working with AFRICURE PHARMA, ROW2TECH, NIPER-G, Department of Pharmaceuticals, Ministry of Chemicals and Fertilizers, Govt. of India as ADVISOR, earlier assignment was with GLENMARK LIFE SCIENCES LTD, as CONSUlTANT, Retired from GLENMARK in Jan2022 Research Centre as Principal Scientist, Process Research (bulk actives) at Mahape, Navi Mumbai, India. Total Industry exp 32 plus yrs, Prior to joining Glenmark, he has worked with major multinationals like Hoechst Marion Roussel, now Sanofi, Searle India Ltd, now RPG lifesciences, etc. He has worked with notable scientists like Dr K Nagarajan, Dr Ralph Stapel, Prof S Seshadri, etc, He did custom synthesis for major multinationals in his career like BASF, Novartis, Sanofi, etc., He has worked in Discovery, Natural products, Bulk drugs, Generics, Intermediates, Fine chemicals, Neutraceuticals, GMP, Scaleups, etc, he is now helping millions, has 9 million plus hits on Google on all Organic chemistry websites. His friends call him Open superstar worlddrugtracker. His New Drug Approvals, Green Chemistry International, All about drugs, Eurekamoments, Organic spectroscopy international, etc in organic chemistry are some most read blogs He has hands on experience in initiation and developing novel routes for drug molecules and implementation them on commercial scale over a 32 PLUS year tenure till date Feb 2023, Around 35 plus products in his career. He has good knowledge of IPM, GMP, Regulatory aspects, he has several International patents published worldwide . He has good proficiency in Technology transfer, Spectroscopy, Stereochemistry, Synthesis, Polymorphism etc., He suffered a paralytic stroke/ Acute Transverse mylitis in Dec 2007 and is 90 %Paralysed, He is bound to a wheelchair, this seems to have injected feul in him to help chemists all around the world, he is more active than before and is pushing boundaries, He has 100 million plus hits on Google, 2.5 lakh plus connections on all networking sites, 100 Lakh plus views on dozen plus blogs, 227 countries, 7 continents, He makes himself available to all, contact him on +91 9323115463, email amcrasto@gmail.com, Twitter, @amcrasto , He lives and will die for his family, 90% paralysis cannot kill his soul., Notably he has 38 lakh plus views on New Drug Approvals Blog in 227 countries......https://newdrugapprovals.wordpress.com/ , He appreciates the help he gets from one and all, Friends, Family, Glenmark, Readers, Wellwishers, Doctors, Drug authorities, His Contacts, Physiotherapist, etc He has total of 32 International and Indian awards

Verified Services

View Full Profile →

Archives

Categories

Flag Counter

Tiny amounts of BPA can alter mammary gland development


Ralph Turchiano's avatarCLINICALNEWS.ORG

Researchers see BPA effects in monkey mammary glands

Study adds to growing health concerns about common plastic additive

PULLMAN, Wash.—A new study finds that fetal exposure to the plastic additive bisphenol A, or BPA, alters mammary gland development in primates. The finding adds to the evidence that the chemical can be causing health problems in humans and bolsters concerns about it contributing to breast cancer.

“Previous studies in mice have demonstrated that low doses of BPA alter the developing mammary gland and that these subtle changes increase the risk of cancer in the adult,” says Patricia Hunt, a geneticist in Washington State University’s School of Molecular Biosciences. “Some have questioned the relevance of these findings in mice to humans. But finding the same thing in a primate model really hits uncomfortably close to home.”

View original post 288 more words

Mom will teach you NMR


Dedicated to all moms in the world
C=O group is dad
O atom is mom
Carbonyl is dad and oxygen mom hence c labelled methyl has higher chemical shift  and gets a little more attention
SEE BELOW
NMR IS EASY
A chemical has Formula: C5H10O2
C5H10O2
Rule 2, omit O, gives C5H10
5 – 10/2 + 1 = 1 degree of unsaturation.
Look for 1 pi bond or aliphatic ring.
IR
IR spectrum
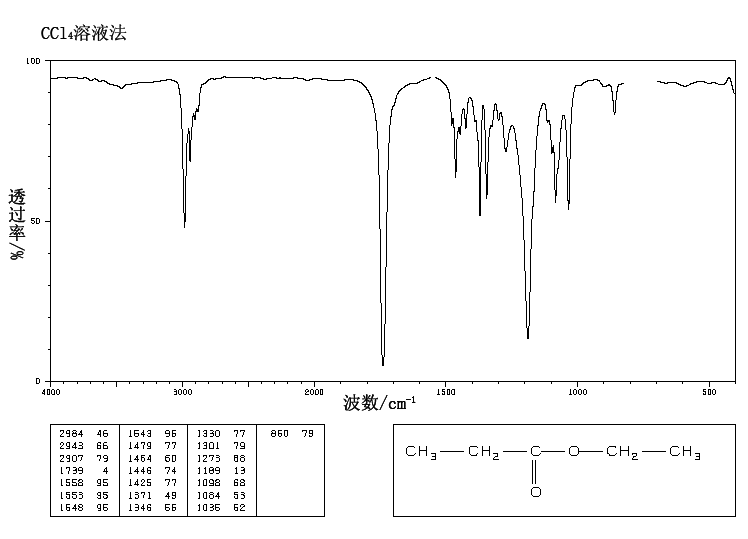
The band at 1740 indicates a carbonyl, probably a saturated aliphatic ester. The bands at 3000-2850 indicate C-H alkane stretches. The bands in the region 1320-1000 could be due to C-O stretch, consistent with an ester.
NMR spectrum
Structure answerThis is the structure. See if you can assign the peaks on your own.
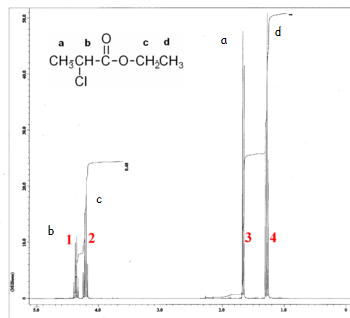
NMR answerC has a higher chemical shift than D because it’s closer to a more electron-withdrawing functional group.
Carbonyl is dad and oxygen mom,  hence c has higher chemical shift  and gets a little more attention in proton nmr
13 C NMR
Mass spectrum
RAMAN
WHAT HAPPENS WHEN A CHLORO IS INTRODUCED
THE INTERPRETATION IS BELOW

remember “a” labelled  CH3 appears as a doublet

WHEN THERE IS ONE METHYL
WHEN THERE ONE CH2 SHORT 
WHEN MOM HAS ONE MORE CH2
PROPYL PROPIONATE, try this on your own
Propyl propanoate.png
1H NMR
image of Propyl proprionatesee interpretation

 BIGGER ONE THAN OBOVE
image of Propyl proprionate
13C NMR
image of Propyl proprionate
APT
image of Propyl proprionate
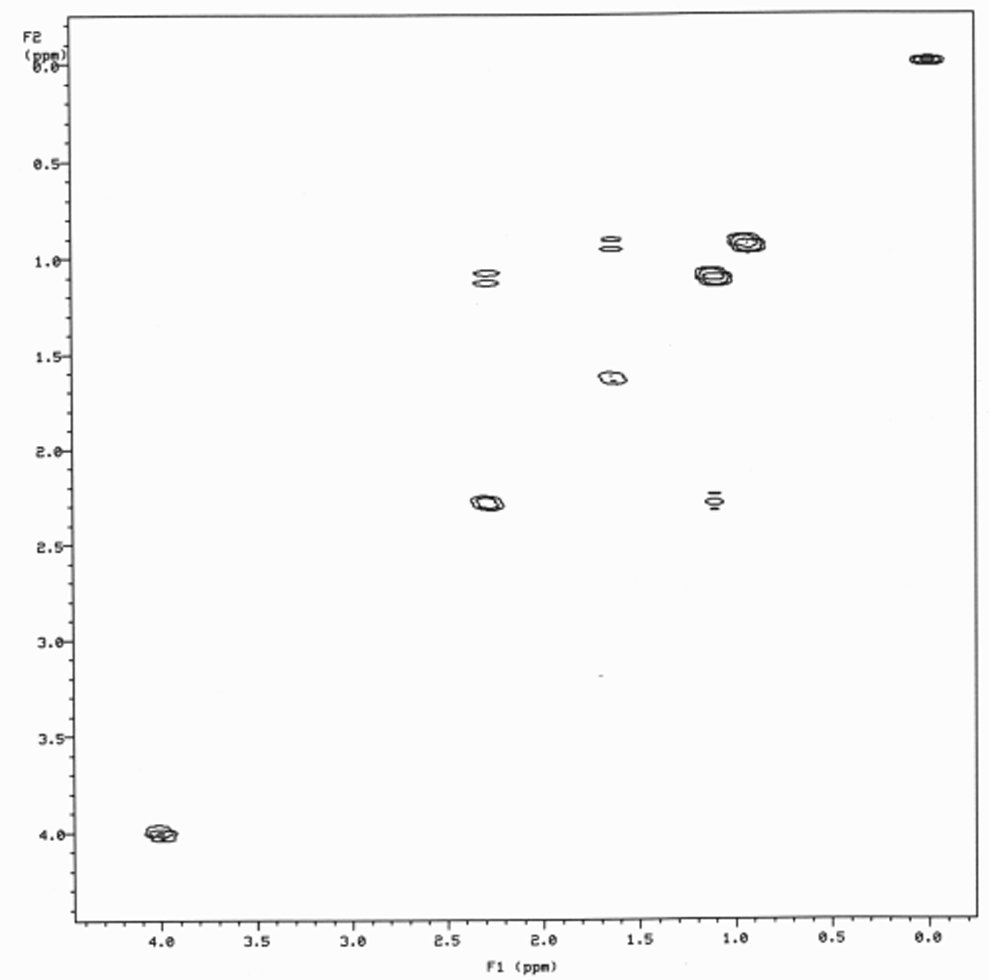
COSY
image of Propyl proprionate
WILL PASTE INTERPRETATION AFTER ONE WEEK……………….

Natural products from plants protect skin during cancer radiotherapy


Ralph Turchiano's avatarCLINICALNEWS.ORG

PUBLIC RELEASE DATE:

24-Jul-2014
Radiotherapy for cancer involves exposing the patient or their tumor more directly to ionizing radiation, such as gamma rays or X-rays. The radiation damages the cancer cells irreparably. Unfortunately, such radiation is also harmful to healthy tissue, particularly the skin over the site of the tumor, which is then at risk of hair loss, dermatological problems and even skin cancer. As such finding ways to protect the overlying skin are keenly sought.

Writing in the International Journal of Low Radiation, Faruck Lukmanul Hakkim of the University of Nizwa, Oman and Nagasaki University, Nagasaki, Japan, and colleagues there and at Macquarie University, New South Wales, Australia, Bharathiar University, India and Konkuk University, South Korea, explain how three ubiquitous and well-studied natural products derived from plants can protect the skin against gamma radiation during radiotherapy.

View original post 295 more words

Sage Therapeutics receives fast track designation for status epilepticus therapy


Allopregnanolone.png

SAGE-547
 ALLOPREGNANOLONE

Sage Therapeutics (Originator)

Sage Therapeutics

For Epilepsy, status epilepticus

SGE-102; SAGE-547; allopregnanolone; allosteric GABA A receptor modulators (CNS disorders),

Sage Therapeutics receives fast track designation for status epilepticus therapy
Ligand Pharmaceuticals announced that its partner Sage Therapeutics has received fast track designation from the US Food and Drug Administration (FDA) for the Captisol-enabled SAGE-547 to treat status epilepticus.

read at

http://www.pharmaceutical-technology.com/news/newssage-therapeutics-receives-fast-track-designation-for-status-epilepticus-therapy-4324543?WT.mc_id=DN_News


Chemical Name:   (3α)-Allopregnanolone
Synonyms:   (+)-3α-Hydroxy-5α-pregnan-20-one; (3α,5α)-3-Hydroxypregnan-20-one; 3α,5α-THP; 3α,5α-Tetrahydroprogesterone; 3α-Hydroxy-5α-dihydroprogesterone; 3α-Hydroxy-5α-pregnan-20-one; 3α-Hydroxy-5α-pregnane-20-one; 5α-Pregnan-3α-ol-20-one; 5α-Pregnane-3α-ol-20-one; Allopregnan-3α-ol-20-one; Allopregnanolone; Allotetrahydroprogesterone;
CAS Number:   516-54-1
Applications:   (3α)-Allopregnanolone acts as a GABAA receptor positive allosteric modulator. (3α)-Allopregnanolone is a metabolite of Progesterone (P755900). (3α)-Allopregnanolone is a neuroactive steroid present in the blood and also the brain.
References:   Puja, G. et al.: Neuron, 4, 759 (1990); Belelli, D. et ael. Neurosteroid, 6, 565 (2006); Viapiano, M. et al.: Neurochem. Res., 23, 155 (1998);
Mol. Formula:   C21H34O2
Appearance:   White Solid
Melting Point:   174-176°C
Mol. Weight:   318.49

SAGE-547 is a GABA(A) receptor modulator in phase I/II clinical trials at Sage Therapeutics as adjunctive therapy for the treatment of adults with super-refractory status epilepticus (SRSE).

In 2014, orphan drug designation was assigned in the U.S for the treatment of status epilepticus. In July 2014, fast track designation was received in the U.S. for the treatment of adults with super-refractory status epilepticus (SRSE).

July 22, 2014

SAGE Therapeutics, a biopharmaceutical company developing novel medicines to treat life-threatening, rare central nervous system (CNS) disorders, announced today that the U.S. Food and Drug Administration (FDA) has granted fast track designation to the SAGE-547 development program. SAGE-547 is an allosteric modulator of GABAA receptors in development for the treatment of adult patients with refractory status epilepticus who have not responded to standard regimens (super-refractory status epilepticus, or SRSE). SAGE is currently evaluating SAGE-547 in a Phase 1/2 clinical trial for the treatment of SRSE. Preliminary data indicate that the first four patients enrolled in the clinical trial met the key efficacy endpoint, in that each was successfully weaned off his or her anesthetic agent while SAGE-547 was being administered. There have also been no reported drug-related serious adverse events in these four patients to date.

“The fast track designation for SAGE-547 recognizes the significant unmet need that exists in the treatment of super-refractory status epilepticus,” said Jeff Jonas, MD, chief executive officer of SAGE Therapeutics. “The receipt of orphan drug designation earlier this year for status epilepticus and the fast track designation are both significant regulatory milestones for SAGE-547, and we will continue to work closely with the FDA to advance our lead compound and the additional programs in our pipeline for the treatment of life-threatening CNS disorders.”

Fast track designation is granted by the FDA to facilitate the development and expedite the review of drug candidates that are intended to treat serious or life-threatening conditions and that demonstrate the potential to address unmet medical needs.

About SAGE-547

SAGE-547 is an allosteric modulator of both synaptic and extra-synaptic GABAA receptors. GABAA receptors are widely regarded as validated drug targets for a variety of CNS disorders, with decades of research and multiple approved drugs targeting these receptor systems. SAGE-547 is an intravenous agent in Phase 1/2 clinical development as an adjunctive therapy, a therapy combined with current therapeutic approaches, for the treatment of SRSE.

About Status Epilepticus (SE)

SE is a life-threatening seizure condition that occurs in approximately 150,000 people each year in the U.S., of which 30,000 SE patients die.1 We estimate that there are 35,000 patients with SE in the U.S. that are hospitalized in the intensive care unit (ICU) each year. An SE patient is first treated with benzodiazepines, and if no response, is then treated with other, second-line, anti-seizure drugs. If the seizure persists after the second-line therapy, the patient is diagnosed as having refractory SE (RSE), admitted to the ICU and placed into a medically induced coma. Currently, there are no therapies that have been specifically approved for RSE; however, physicians typically use anesthetic agents to induce the coma and stop the seizure immediately. After a period of 24 hours, an attempt is made to wean the patient from the anesthetic agents to evaluate whether or not the seizure condition has resolved. Unfortunately, not all patients respond to weaning attempts, in which case the patient must be maintained in the medically induced coma. At this point, the patient is diagnosed as having SRSE. Currently, there are no therapies specifically approved for SRSE.

About SAGE Therapeutics

SAGE Therapeutics (NASDAQ: SAGE) is a biopharmaceutical company committed to developing and commercializing novel medicines to treat life-threatening, rare CNS disorders. SAGE’s lead program, SAGE-547, is in clinical development for super-refractory status epilepticus and is the first of several compounds the company is developing in its portfolio of potential seizure medicines. SAGE’s proprietary chemistry platform has generated multiple new compounds that target GABAA and NMDA receptors, which are broadly accepted as impacting many psychiatric and neurological disorders. SAGE Therapeutics is a public company launched in 2010 by an experienced team of R&D leaders, CNS experts and investors. For more information, please visitwww.sagerx.com.

Allopregnanolone
Allopregnanolone.png
Identifiers
PubChem 262961
ChemSpider 17216124 Yes
ChEMBL CHEMBL38856 
Jmol-3D images Image 1
Properties
Molecular formula C21H34O2
Molar mass 318.49 g/mol


Allopregnanolone (3α-hydroxy-5α-pregnan-20-one or 3α,5α-tetrahydroprogesterone), generally abbreviated as ALLO or as 3α,5α-THP, is an endogenous inhibitory pregnane neurosteroid.[1] It is synthesized from progesterone, and is a potent positive allosteric modulator of the GABAA receptor.[1] Allopregnanolone has effects similar to those of other potentiators of the GABAA receptor such as the benzodiazepines, including anxiolytic, sedative, and anticonvulsant activity.[1]

The 21-hydroxylated derivative of this compound, tetrahydrodeoxycorticosterone (THDOC), is an endogenous inhibitory neurosteroid with similar properties to those of allopregnanolone, and the 3β-methyl analogue of allopregnanolone, ganaxolone, is under development to treat epilepsy and other conditions.[1]

Biosynthesis

The biosynthesis of allopregnanolone starts with the conversion of progesterone into 5α-dihydroprogesterone by 5α-reductase type I. After that, 3α-hydroxysteroid dehydrogenase converts this intermediate into allopregnanolone.[1]

Depression, anxiety, and sexual dysfunction are frequently-seen side effects of 5α-reductase inhibitors such as finasteride, and are thought to be caused, in part, by interfering with the normal production of allopregnanolone.[2]

Mechanism

Allopregnanolone acts as a potent positive allosteric modulator of the GABAA receptor.[1] While allopregnanolone, like other inhibitory neurosteroids such as THDOC, positively modulates all GABAA receptor isoforms, those isoforms containing δ subunits exhibit the greatest potentiation.[1] Allopregnanolone has also been found to act as a positive allosteric modulator of the GABAA-ρ receptor, though the implications of this action are unclear.[3][4] In addition to its actions on GABA receptors, allopregnanolone, like progesterone, is known to be a negative allosteric modulator of nACh receptors,[5] and also appears to act as a negative allosteric modulator of the 5-HT3 receptor.[6] Along with the other inhibitory neurosteroids, allopregnanolone appears to have little or no action at other ligand-gated ion channels, including the NMDA, AMPA, kainate, and glycine receptors.[7]

Unlike progesterone, allopregnanolone is inactive at the nuclear progesterone receptor (nPR).[7] However, allopregnanolone can be intracellularly oxidized into 5α-dihydroprogesterone, which is an agonist of the nPR, and thus/in accordance, allopregnanolone does appear to have indirect nPR-mediated progestogenic effects.[8] In addition, allopregnanolone has recently been found to be an agonist of the newly-discovered membrane progesterone receptors (mPR), including mPRδ, mPRα, and mPRβ, with its activity at these receptors about a magnitude more potent than at the GABAA receptor.[9][10] The action of allopregnanolone at these receptors may be related, in part, to its neuroprotective and antigonadotropic properties.[9][11] Also like progesterone, recent evidence has shown that allopregnanolone is an activator of the pregnane X receptor.[7][12]

Similarly to many other GABAA receptor positive allosteric modulators, allopregnanolone has been found to act as an inhibitor of L-type voltage-gated calcium channels (L-VGCCs),[13] including α1 subtypes Cav1.2 and Cav1.3.[14] However, the threshold concentration of allopregnanolone to inhibit L-VGCCs was determined to be 3 μM (3,000 nM), which is far greater than the concentration of 5 nM that has been estimated to be naturally produced in the human brain.[14] Thus, inhibition of L-VGCCs is unlikely of any actual significance in the effects of endogenous allopregnanolone.[14] Also, allopregnanolone, along with several other neurosteroids, has been found to activate the G protein-coupled bile acid receptor (GPBAR1, or TGR5).[15] However, it is only able to do so at micromolar concentrations, which, similarly to the case of the L-VGCCs, are far greater than the low nanomolar concentrations of allopregnanolone estimated to be present in the brain.[15]

Function

Allopregnanolone possesses a wide variety of effects, including, in no particular order, antidepressant, anxiolytic, stress-reducing, rewarding,[16] prosocial,[17] antiaggressive,[18] prosexual,[17] sedative, pro-sleep,[19] cognitive and memory-impairing, analgesic,[20] anesthetic, anticonvulsant, neuroprotective, and neurogenic effects.[1]

Fluctuations in the levels of allopregnanolone and the other neurosteroids seem to play an important role in the pathophysiology of mood, anxiety, premenstrual syndrome, catamenial epilepsy, and various other neuropsychiatric conditions.[21][22][23]

Increased levels of allopregnanolone can produce paradoxical effects, including negative mood, anxiety, irritability, and aggression.[24][25][26] This appears to be because allopregnanolone possesses biphasic, U-shaped actions at the GABAA receptor – moderate level increases (in the range of 1.5–2 nM/L total allopregnanolone, which are approximately equivalent to luteal phase levels) inhibit the activity of the receptor, while lower and higher concentration increases stimulate it.[24][25] This seems to be a common effect of many GABAA receptor positive allosteric modulators.[26][21] In accordance, acute administration of low doses of micronized progesterone (which reliably elevates allopregnanolone levels), have been found to have negative effects on mood, while higher doses have a neutral effect.[27]

Therapeutic applications

Allopregnanolone and the other endogenous inhibitory neurosteroids have very short half-lives, and for this reason, have not been pursued for clinical use themselves. Instead, synthetic analogs with improved pharmacokinetic profiles, such as ganaxolone, have been synthesized and are being investigated. However, exogenous progesterone, such as oral micronized progesterone (OMP), reliably elevates allopregnanolone levels in the body with good dose-to-serum level correlations.[28] Due to this, it has been suggested that OMP could be described as a prodrug of sorts for allopregnanolone.[28] As a result, there has been some interest in using OMP to treat catamenial epilepsy,[29] as well as other menstrual cycle-related and neurosteroid-associated conditions.

……………………………………….

http://www.google.com/patents/WO2006037016A2?cl=en

Materials and Methods

[0181] The materials and methods used for the follwing experiments have been described in Griffin L.D., et al, Nature Medicine 10: 704-711 (2004). This reference is hereby incorporated by reference in its entirety.

Example 1: Allopregnanolone Treatment of Niemann Pick type-C Mice Substantially Reduces Accumulation of the Gangliosides GMl, GM2, and GM3 in the Brain [0182] Mice were given a single injection of allopregnanolone, prepared in 20% βcyclodextrin in phosphate buffered saline, at a concentration of 25 mg/kg. The injection was on day 7 of life (P7, postnatal day 7). Concentrations of gangliosides GMl, GM2, GM3, were measured as well as other lipids such as ceramides and cerebrosides.

…………………………………………….

WO-2014031792 OR EQ

http://www.google.com/patents/US20140057885?cl=en

…………………………………….

WO-2013112605

http://www.google.com/patents/WO2013112605A2?cl=en

References

  1. Reddy DS (2010). “Neurosteroids: endogenous role in the human brain and therapeutic potentials”. Prog. Brain Res. 186: 113–37. doi:10.1016/B978-0-444-53630-3.00008-7. PMC 3139029. PMID 21094889.
  2. Römer B, Gass P (December 2010). “Finasteride-induced depression: new insights into possible pathomechanisms”. J Cosmet Dermatol 9 (4): 331–2. doi:10.1111/j.1473-2165.2010.00533.x. PMID 21122055.
  3. Morris KD, Moorefield CN, Amin J (October 1999). “Differential modulation of the gamma-aminobutyric acid type C receptor by neuroactive steroids”. Mol. Pharmacol. 56 (4): 752–9. PMID 10496958.
  4. Li W, Jin X, Covey DF, Steinbach JH (October 2007). “Neuroactive steroids and human recombinant rho1 GABAC receptors”. J. Pharmacol. Exp. Ther. 323 (1): 236–47. doi:10.1124/jpet.107.127365. PMID 17636008.
  5. Bullock AE, Clark AL, Grady SR, et al. (June 1997). “Neurosteroids modulate nicotinic receptor function in mouse striatal and thalamic synaptosomes”. J. Neurochem. 68 (6): 2412–23. PMID 9166735.
  6. Wetzel CH, Hermann B, Behl C, et al. (September 1998). “Functional antagonism of gonadal steroids at the 5-hydroxytryptamine type 3 receptor”. Mol. Endocrinol. 12 (9): 1441–51. doi:10.1210/mend.12.9.0163. PMID 9731711.
  7. Mellon SH (October 2007). “Neurosteroid regulation of central nervous system development”. Pharmacol. Ther. 116 (1): 107–24. doi:10.1016/j.pharmthera.2007.04.011. PMC 2386997. PMID 17651807.
  8. Rupprecht R, Reul JM, Trapp T, et al. (September 1993). “Progesterone receptor-mediated effects of neuroactive steroids”. Neuron 11 (3): 523–30. PMID 8398145.
  9. Thomas P, Pang Y (2012). “Membrane progesterone receptors: evidence for neuroprotective, neurosteroid signaling and neuroendocrine functions in neuronal cells”. Neuroendocrinology 96 (2): 162–71. doi:10.1159/000339822. PMC 3489003. PMID 22687885.
  10. Pang Y, Dong J, Thomas P (January 2013). “Characterization, neurosteroid binding and brain distribution of human membrane progesterone receptors δ and {epsilon} (mPRδ and mPR{epsilon}) and mPRδ involvement in neurosteroid inhibition of apoptosis”. Endocrinology 154 (1): 283–95. doi:10.1210/en.2012-1772. PMC 3529379. PMID 23161870.
  11. Sleiter N, Pang Y, Park C, et al. (August 2009). “Progesterone receptor A (PRA) and PRB-independent effects of progesterone on gonadotropin-releasing hormone release”. Endocrinology 150 (8): 3833–44. doi:10.1210/en.2008-0774. PMC 2717864. PMID 19423765.
  12. Lamba V, Yasuda K, Lamba JK, et al. (September 2004). “PXR (NR1I2): splice variants in human tissues, including brain, and identification of neurosteroids and nicotine as PXR activators”. Toxicol. Appl. Pharmacol. 199 (3): 251–65. doi:10.1016/j.taap.2003.12.027. PMID 15364541.
  13. Hu AQ, Wang ZM, Lan DM, et al. (July 2007). “Inhibition of evoked glutamate release by neurosteroid allopregnanolone via inhibition of L-type calcium channels in rat medial prefrontal cortex”. Neuropsychopharmacology 32 (7): 1477–89. doi:10.1038/sj.npp.1301261. PMID 17151597.
  14. Earl DE, Tietz EI (April 2011). “Inhibition of recombinant L-type voltage-gated calcium channels by positive allosteric modulators of GABAA receptors”. J. Pharmacol. Exp. Ther. 337 (1): 301–11. doi:10.1124/jpet.110.178244. PMC 3063747. PMID 21262851.
  15. Keitel V, Görg B, Bidmon HJ, et al. (November 2010). “The bile acid receptor TGR5 (Gpbar-1) acts as a neurosteroid receptor in brain”. Glia 58 (15): 1794–805. doi:10.1002/glia.21049. PMID 20665558.
  16. Rougé-Pont F, Mayo W, Marinelli M, Gingras M, Le Moal M, Piazza PV (July 2002). “The neurosteroid allopregnanolone increases dopamine release and dopaminergic response to morphine in the rat nucleus accumbens”. Eur. J. Neurosci. 16 (1): 169–73. PMID 12153544.
  17. Frye CA (December 2009). “Neurosteroids’ effects and mechanisms for social, cognitive, emotional, and physical functions”. Psychoneuroendocrinology. 34 Suppl 1: S143–61. doi:10.1016/j.psyneuen.2009.07.005. PMC 2898141. PMID 19656632.
  18. Pinna G, Costa E, Guidotti A (February 2005). “Changes in brain testosterone and allopregnanolone biosynthesis elicit aggressive behavior”. Proc. Natl. Acad. Sci. U.S.A. 102 (6): 2135–40. doi:10.1073/pnas.0409643102. PMC 548579. PMID 15677716.
  19. Terán-Pérez G, Arana-Lechuga Y, Esqueda-León E, Santana-Miranda R, Rojas-Zamorano JÁ, Velázquez Moctezuma J (October 2012). “Steroid hormones and sleep regulation”. Mini Rev Med Chem 12 (11): 1040–8. PMID 23092405.
  20. Patte-Mensah C, Meyer L, Taleb O, Mensah-Nyagan AG (February 2014). “Potential role of allopregnanolone for a safe and effective therapy of neuropathic pain”. Prog. Neurobiol. 113: 70–8. doi:10.1016/j.pneurobio.2013.07.004. PMID 23948490.
  21. Bäckström T, Andersson A, Andreé L, et al. (December 2003). “Pathogenesis in menstrual cycle-linked CNS disorders”. Ann. N. Y. Acad. Sci. 1007: 42–53. PMID 14993039.
  22. Guille C, Spencer S, Cavus I, Epperson CN (July 2008). “The role of sex steroids in catamenial epilepsy and premenstrual dysphoric disorder: implications for diagnosis and treatment”. Epilepsy Behav 13 (1): 12–24. doi:10.1016/j.yebeh.2008.02.004. PMID 18346939.
  23. Finocchi C, Ferrari M (May 2011). “Female reproductive steroids and neuronal excitability”. Neurol. Sci. 32 Suppl 1: S31–5. doi:10.1007/s10072-011-0532-5. PMID 21533709.
  24. Bäckström T, Haage D, Löfgren M, et al. (September 2011). “Paradoxical effects of GABA-A modulators may explain sex steroid induced negative mood symptoms in some persons”. Neuroscience 191: 46–54. doi:10.1016/j.neuroscience.2011.03.061. PMID 21600269.
  25. Andréen L, Nyberg S, Turkmen S, van Wingen G, Fernández G, Bäckström T (September 2009). “Sex steroid induced negative mood may be explained by the paradoxical effect mediated by GABAA modulators”. Psychoneuroendocrinology 34 (8): 1121–32. doi:10.1016/j.psyneuen.2009.02.003. PMID 19272715.
  26. Bäckström T, Bixo M, Johansson M, et al. (February 2014). “Allopregnanolone and mood disorders”. Prog. Neurobiol. 113: 88–94. doi:10.1016/j.pneurobio.2013.07.005. PMID 23978486.
  27. Andréen L, Sundström-Poromaa I, Bixo M, Nyberg S, Bäckström T (August 2006). “Allopregnanolone concentration and mood–a bimodal association in postmenopausal women treated with oral progesterone”. Psychopharmacology (Berl.) 187 (2): 209–21. doi:10.1007/s00213-006-0417-0. PMID 16724185.
  28. Andréen L, Spigset O, Andersson A, Nyberg S, Bäckström T (June 2006). “Pharmacokinetics of progesterone and its metabolites allopregnanolone and pregnanolone after oral administration of low-dose progesterone”. Maturitas 54 (3): 238–44. doi:10.1016/j.maturitas.2005.11.005. PMID 16406399.
  29. Orrin Devinsky; Steven Schachter; Steven Pacia (1 January 2005). Complementary and Alternative Therapies for Epilepsy. Demos Medical Publishing. pp. 378–. ISBN 978-1-934559-08-6.

Additional reading

  • Herd, MB; Belelli, D; Lambert, JJ (2007). Neurosteroid modulation of synaptic and extrasynaptic GABA(A) receptors. Pharmacol. Ther. 116(1):20-34. doi:10.1016/j.pharmthera.2007.03.007.
Deoxyribonucleic acid (DNA) synthesis


Deoxyribonucleic acid (DNA) synthesis is a process by which copies of nucleic acid strands are made. In nature, DNA synthesis takes place in cells by a mechanism known as DNA replication. Using genetic engineering and enzyme chemistry, scientists have developed man-made methods for synthesizing DNA. The most important of these is poly-merase chain reaction (PCR). First developed in the early 1980s, PCR has become a multi-billion dollar industry with the original patent being sold for $300 million dollars.

read all at

Read more: http://www.madehow.com/Volume-6/DNA-Synthesis.html#ixzz38Gx0QqXK

Read more: http://www.madehow.com/Volume-6/DNA-Synthesis.html#ixzz38GwuVHeO

http://www.madehow.com/Volume-6/DNA-Synthesis.html

DNA synthesis

From Wikipedia, the free encyclopedia

DNA synthesis is the natural or artificial creation of deoxyribonucleic acid (DNA) molecules. The term DNA synthesis can refer to any of the following in various contexts:


DNA replication

In nature, such molecules are created by all living cells through the process of DNA replication, with replication initiator proteins splitting the existing DNA of the cell and making a copy of each split strand, with the copied strands then being joined together with their template strand into a new DNA molecule. Various means also exist to artificially stimulate the replication of naturally occurring DNA, or to create artificial gene sequences.

Polymerase chain reaction

A polymerase chain reaction is a form of enzymatic DNA synthesis in the laboratory, using cycles of repeated heating and cooling of the reaction for DNA melting and enzymatic replication of the DNA.

Gene synthesis

Artificial gene synthesis is the process of synthesizing a gene in vitro without the need for initial template DNA samples. In 2010 J. Craig Venter and his team were the first to use entirely synthesized DNA to create a self-replicating microbe, dubbed Mycoplasma laboratorium.[1]

Oligonucleotide synthesis

Oligonucleotide synthesis is the chemical synthesis of sequences of nucleic acids. The process has been fully automated since the late 1970s and can be used to form desired genetic sequences as well as for other uses in medicine and molecular biology.

Base pair synthesis

Recent research has demonstrated the possibility of creating new nucleobase pairs in addition to the naturally occurring pairs, A-T (adenine – thymine) and G-C (guanine –cytosine). A third base pair could dramatically expand the number of amino acids that can be encoded by DNA, from the existing 20 amino acids to a theoretically possible 172.[1]

References

  1. ^ Jump up to:a b Fikes, Bradley J. (May 8, 2014). “Life engineered with expanded genetic code”. San Diego Union Tribune. Retrieved 8 May 2014.

Pixantrone


Chemical structure for CTK0H5262


Pixantrone.svg

Pixantrone

BBR-2778 , CTK0H5262


  • Pixolti
  • Pixuvri
  • UNII-P0R64C4CR9


An immunosuppressant.

144510-96-3 [RN]

5,8-Bis((2-aminoethyl)amino)-2-aza-anthracene-9,10-dione

6,9-Bis((2-aminoethyl)amino)benz(g)isoquinoline-5,10-dione

5,8-Bis((2-aminoethyl)amino)-2-aza-anthracene-9,10-dione

6,9-Bis((2-aminoethyl)amino)benz(g)isoquinoline-5,10-dione

CTI BioPharma receives Israeli approval for aggressive B-cell non-Hodgkin’s lymphoma therapy

CTI BioPharma has obtained Israeli Ministry of Health’s approval for Pixuvri (pixantrone), as a monotherapy to treat adult patients with multiply relapsed or refractory aggressive B-cell non-Hodgkin’s lymphoma who have received up to three previous courses of treatment.

The company also announced that the Dutch Healthcare Authority and the College voor zorgverzekeringen of the Netherlands have approved funding for Pixuvri as an add-on drug for patients who need a third or fourth-line treatment option for aggressive B-cell lymphoma.

Tel Aviv University faculty of medicine Dr Abraham Avigdor said: “The approval of PIXUVRI in Israel provides patients with aggressive B-cell NHL who have failed second or third-line therapy a new approved option, where none existed before, that can effectively treat their disease with manageable side-effects.


read at

http://www.pharmaceutical-technology.com/news/newscti-biopharma-receives-israeli-approval-aggressive-b-cell-non-hodgkins-lymphoma-therapy-4321986?WT.mc_id=DN_News


Pixantrone
Pixantrone.svg
Identifiers
CAS number  144510-96-3
PubChem 134019
ChemSpider 118174 Yes
KEGG D05522 Yes
ChEMBL CHEMBL167731 Yes
ATC code L01DB11
Jmol-3D images Image 1
Properties
Molecular formula C17H19N5O2
Molar mass 325.365 g/mol
Appearance Blue solid
Pharmacology
Routes of
administration
Intravenous
Elimination
half-life
9.5–17.5 hours
Excretion Fecal (main route of excretion) and renal (4–9%)
Except where noted otherwise, data are given for materials in their standard state (at 25 °C (77 °F), 100 kPa)

Pixantrone dimaleate [USAN]

CAS  144675-97-8

Molecular Formula

  • C17-H19-N5-O2.2C4-H4-O4

Molecular Weight

  • 441.4417
  • Benz(g)isoquinoline-5,10-dione, 6,9-bis((2-aminoethyl)amino)-, (2Z)-2-butenedioate (1:2)

On May 10, 2012, the European Commission issued a conditional marketing authorization valid throughout the European Union for pixantrone for the treatment of adult patients with multiply relapsed or refractory aggressive non-Hodgkin’s B-cell lymphoma (NHL). Pixantrone is a cytotoxic aza-anthracenedione that directly alkylates DNA-forming stable DNA adducts and cross-strand breaks. The recommended dose of pixantrone is 50 mg/m2 administered on days 1, 8, and 15 of each 28-day cycle for up to 6 cycles. In the main study submitted for this application, a significant difference in response rate (proportion of complete responses and unconfirmed complete responses) was observed in favor of pixantrone (20.0% vs. 5.7% for pixantrone and physician’s best choice, respectively), supported by the results of secondary endpoints of median progression-free and overall survival times (increase of 2.7 and 2.6 months, respectively). The most common side effects with pixantrone were bone marrow suppression (particularly of the neutrophil lineage) nausea, vomiting, and asthenia. This article summarizes the scientific review of the application leading to approval in the European Union. The detailed scientific assessment report and product information, including the summary of product characteristics, are available on the European Medicines Agency website (http://www.ema.europa.eu).


Pixantrone (rINN; trade name Pixuvri) is an experimental antineoplastic (anti-cancer) drug, an analogue of mitoxantrone with fewertoxic effects on cardiac tissue.[1] It acts as a topoisomerase II poison and intercalating agent.[2][3] The code name BBR 2778 refers topixantrone dimaleate, the actual substance commonly used in clinical trials.[4]


History

Anthracyclines are important chemotherapy agents. However, their use is associated with irreversible and cumulative heart damage. Investigators have attempted to design related drugs that maintain the biological activity, but do not possess the cardiotoxicity of the anthracyclines.[5] Pixantrone was developed to reduce heart damage related to treatment while retaining efficacy.[1]

Random screening at the US National Cancer Institute of a vast number of compounds provided by the Allied Chemical Company led to the discovery of ametantrone as having significant anti-tumor activity. Further investigation regarding the rational development of analogs of ametantrone led to the synthesis of mitoxantrone, which also exhibited marked anti-tumor activity[5] Mitoxantrone was considered as an analog of doxorubicin with less structural complexity but with a similar mode of action. In clinical studies, mitoxantrone was shown to be effective against numerous types of tumors with less toxic side effects than those resulting from doxorubicin therapy. However, mitoxantrone was not totally free of cardiotoxicity. A number of structurally modified analogs of mitoxantrone were synthesized and structure-activity relationship studies made.[5] BBR 2778 was originally synthesized by University of Vermont researchers Miles P. Hacker and Paul A. Krapcho[5] and initially characterized in vitro for tumor cell cytotoxicity and mechanism of action by studies at the Boehringer Mannheim Italia Research Center, Monza, and University of Vermont, Burlington.[4]Other studies have been completed at the University of Texas M. D. Anderson Cancer Center, Houston, the Istituto Nazionale Tumori,Milan, and the University of Padua.[2][6][4] In the search for novel heteroanalogs of anthracenediones, it was selected as the most promising compound. Toxicological studies indicated that BBR 2778 was not cardiotoxic, and US patents are held by the University of Vermont. An additional US patent application was completed in June 1995 by Boehringer Mannheim, Italy.[5]

Novuspharma, an Italian company, was established in 1998 following the merger of Boehringer Mannheim and Hoffmann-La Roche, and BBR 2778 was developed as Novuspharma’s leading anti-cancer drug, pixantrone.[7] A patent application for the injectable preparation was filed in May 2003.[8]

In 2003, Cell Therapeutics, a Seattle biotechnology company, acquired pixantrone through a merger with Novuspharma.[9]

Clinical trials

Pixantrone is a substance that is being studied in the treatment of cancer. It belongs to the family of drugs called antitumor antibiotics.[10] phase III clinical trials of pixantrone have been completed.[11][12] Pixantrone is being studied as an antineoplastic for different kinds of cancer, including solid tumors and hematological malignancies such as non-Hodgkin lymphomas.

Animal studies demonstrated that pixantrone does not worsen pre-existing heart muscle damage, suggesting that pixantrone may be useful in patients pretreated with anthracyclines. While only minimal cardiac changes are observed in mice given repeated cycles of pixantrone, 2 cycles of traditional anthracyclines doxorubicin or mitoxantrone result in marked or severe heart muscle degeneragion.[1]

Clinical trials substituting pixantrone for doxorubicin in standard first-line treatment of patients with aggressive non-Hodgkin’s lymphoma, had a reduction in severe side effects when compared to patients treated with standard doxorubicin-based therapy. Despite pixantrone patients receiving more treatment cycles, a three-fold reduction in the incidence of severe heart damage was seen as well as clinically significant reductions in infections and thrombocytopenia, and a significant reduction in febrile neutropenia. These findings could have major implications for treating patients with breast cancer, lymphoma, and leukemia, where debilitating cardiac damage from doxorubicin might be prevented.[13]Previous treatment options for multiply relapsed aggressive non-Hodgkin lymphoma had disappointing response rates.[14]

The completed phase II RAPID trial compared the CHOP-R regimen of Cyclophosphamide, Doxorubicin, Vincristine, Prednisone, and Rituximab to the same regimen, but substituting Doxorubicin with Pixantrone. The objective was to show that Pixantrone was not inferior to Doxorubicin and less toxic to the heart.[15]

Pixantrone was shown to have potentially reduced cardiotoxicity and demonstrated promising clinical activity in these phase II studies in heavily pretreated non-Hodgkin lymphomapatients.[14]

The pivotal phase III EXTEND (PIX301) randomized clinical trial studied pixantrone to see how well it works compared to other chemotherapy drugs in treating patients with relapsed non-Hodgkin’s lymphoma.[16] The complete response rate in patients treated with pixantrone has been significantly higher than in those receiving other chemotherapeutic agents for treatment of relapsed/refractory aggressive non-Hodgkin lymphoma.[14]

Administration

It can be administered through a peripheral vein rather than a central implanted catheter as required for other similar drugs.[8][14]

Regulatory approval

U.S. Food and Drug Administration

The FDA granted fast track designation for pixantrone in patients who had previously been treated two or more times for relapsed or refractory aggressive NHL. Study sponsor Cell Therapeutics announced that Pixantrone achieved the primary efficacy endpoint. The minutes of the Oncologic Drugs Advisory Committee meeting of March 22, 2010[17]show that this had not in fact been achieved with statistical significance and this combined with major safety concerns lead to the conclusion that the trial was not sufficient to support approval. In April 2010 the FDA asked for an additional trial.[18]

European Medicines Agency

On May 5, 2009, Pixantrone became available in Europe on a Named-Patient Basis. A named-patient program is a compassionate use drug supply program under which physicians can legally supply investigational drugs to qualifying patients. Under a named-patient program, investigational drugs can be administered to patients who are suffering from serious illnesses prior to the drug being approved by the European Medicines Evaluation Agency. “Named-patient” distribution refers to the distribution or sale of a product to a specific healthcare professional for the treatment of an individual patient. In Europe, under the named-patient program the drug is most often purchased through the national health system.[19] In 2012 pixantrone received conditional marketing authorization in the European Union as Monotherapy to Treat Adult Patients with Multiply Relapsed or Refractory Aggressive Non-Hodgkin B-Cell Lymphomas.

Research

Pixantrone is as potent as mitoxantrone in animal models of multiple sclerosis.[20] Pixantrone has a similar mechanism of action as mitoxantrone on the effector function of lymphomonocyte B and T cells in experimental allergic encephalomyelitis but with lower cardiotoxicity. Pixantrone inhibits antigen specific and mitogen induced lymphomononuclear cell proliferation, as well as IFN-gamma production.[21] Clinical trials are currently ongoing in Europe.

Pixantrone also reduces the severity of experimental autoimmune myasthenia gravis in Lewis rats,[22] and in vitro cell viability experiments indicated that Pixantrone significantly reduces amyloid beta (A beta(1-42)) neurotoxicity, a mechanism implicated in Alzheimer’s disease.[23]


http://www.chemdrug.com/databases/8_0_mhpyqlxgrykqdwig.html

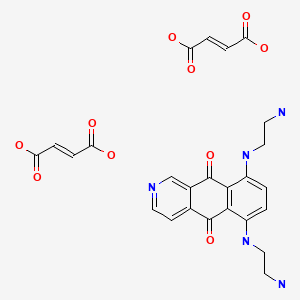
3,4-Pyridinedicarboxylic acid (I) was converted to the cyclic anhydride (II) upon heating with acetic anhydride. Friedel-Crafts condensation of anhydride (II) with p-difluorobenzene (III) in the presence of AlCl3 gave rise to a mixture of two regioisomeric keto acids, (IV) and (V). Cyclization of this mixture in fuming sulfuric acid at 140 C generated the benzoisoquinoline (VI) (1,2). Subsequent displacement of the fluorine atoms of (VI) with ethylenediamine ( VII) in pyridine provided the target bis (2-aminoethylamino) derivative, which was finally converted to the stable dimaleate salt. Alternatively, ethylenediamine (VII) was protected as the mono-N-Boc derivative (VIII) by treatment with Boc2O. Condensation of the difluoro compound (VI) with the protected ethylenediamine (VIII) furnished (IX). The Boc groups of (IX) were then removed by treatment with trifluoroacetic acid. After adjustment of the pH to 4.2 with KOH, treatment with maleic acid provided BBR-2778.

J Med Chem1994,37, (6): 828

SEE MORE

http://www.chemdrug.com/databases/8_0_mhpyqlxgrykqdwig.html

References

  1.  Cavalletti E, Crippa L, Mainardi P, Oggioni N, Cavagnoli R, Bellini O, Sala F. (2007). “Pixantrone (BBR 2778) has reduced cardiotoxic potential in mice pretreated with doxorubicin: comparative studies against doxorubicin and mitoxantrone”. Invest New Drugs. 25 (3): 187–95. doi:10.1007/s10637-007-9037-8. PMID 17285358.
  2. De Isabella P, Palumbo M, Sissi C, Capranico G, Carenini N, Menta E, Oliva A, Spinelli S, Krapcho AP, Giuliani FC, Zunino F. (1995). “Topoisomerase II DNA cleavage stimulation, DNA binding activity, cytotoxicity, and physico-chemical properties of 2-aza- and 2-aza-oxide-anthracenedione derivatives”. Mol Pharmacol. 48 (1): 30–8.PMID 7623772.
  3.  Evison BJ, Mansour OC, Menta E, Phillips DR, Cutts SM (2007). “Pixantrone can be activated by formaldehyde to generate a potent DNA adduct forming agent”. Nucleic Acids Res. 35 (11): 3581–9. doi:10.1093/nar/gkm285. PMC 1920253.PMID 17483512.
  4.  Krapcho AP, Petry ME, Getahun Z, Landi JJ Jr, Stallman J, Polsenberg JF, Gallagher CE, Maresch MJ, Hacker MP, Giuliani FC, Beggiolin G, Pezzoni G, Menta E, Manzotti C, Oliva A, Spinelli S, Tognella S (1994). “6,9-Bis[(aminoalkyl)amino]benzo[g]isoquinoline-5,10-diones. A novel class of chromophore-modified antitumor anthracene-9,10-diones: synthesis and antitumor evaluations”. J Med Chem. 37 (6): 828–37. doi:10.1021/jm00032a018. PMID 8145234.
  5.  US patent 5587382, Krapcho AP, Hacker MP, Cavalletti E, Giuliani FC, “6,9-bis[(2-aminoethyl) amino]benzo [g]isoquinoline-5,10- dione dimaleate; an aza-anthracenedione with reduced cardiotoxicity”, issued 1996-12-24, assigned to Boehringer Mannheim Italia, SpA
  6.  Zwelling LA, Mayes J, Altschuler E, Satitpunwaycha P, Tritton TR, Hacker MP. (1993). “Activity of two novel anthracene-9,10-diones against human leukemia cells containing intercalator-sensitive or -resistant forms of topoisomerase II”. Biochem Pharmacol. 46 (2): 265–71. doi:10.1016/0006-2952(93)90413-Q. PMID 8394077.
  7.  Borchmann P, Reiser M (May 2003). “Pixantrone (Novuspharma)”. IDrugs 6 (5): 486–90. PMID 12789604.
  8.  EP patent 1503797, Bernareggi A, Livi V, “Injectable Pharmaceutical Compositions of an Anthracenedione Derivative with Anti-Tumoral Activity”, published 2003-11-27, issued 2008-09-29, assigned to Cell Therapeutics Europe S.R.L.
  9.  Pollack, Andrew (2003-06-17). “Company News; Cell Therapeutics Announces Plan To Buy Novuspharma”. The New York Times. Retrieved 2010-05-22.
  10. Jump up^ Mosby’s Medical Dictionary, 8th edition. © 2009, Elsevier. “definition of antineoplastic antibiotic”. Free Online Medical Dictionary, Thesaurus and Encyclopedia. Retrieved 2012-01-31.
  11. Jump up^ “NCT00088530”. BBR 2778 for Relapsed, Aggressive Non-Hodgkin’s Lymphoma (NHL). ClinicalTrials.gov. Retrieved 2012-01-31.
  12.  “NCT00551239”. Fludarabine and Rituximab With or Without Pixantrone in Treating Patients With Relapsed or Refractory Indolent Non-Hodgkin Lymphoma. ClinicalTrials.gov. 2012-01-31. Retrieved 2012-01-31.
  13. “Pixantrone Combination Therapy for First-line Treatment of Aggressive Non-Hodgkin’s Lymphoma Results in Reduction in Severe Toxicities Including Heart Damage When Compared to Doxorubicin-based Therapy”. Press Release. Retrieved 2012-01-31.
  14. ^ Jump up to:a b c d Engert A, Herbrecht R, Santoro A, Zinzani PL, Gorbatchevsky I (September 2006). “EXTEND PIX301: a phase III randomized trial of pixantrone versus other chemotherapeutic agents as third-line monotherapy in patients with relapsed, aggressive non-Hodgkin’s lymphoma”. Clin Lymphoma Myeloma 7 (2): 152–4.doi:10.3816/CLM.2006.n.055. PMID 17026830.
  15. Jump up^ “NCT00268853”. A Trial in Patients With Diffuse Large-B-cell Lymphoma Comparing Pixantrone Against Doxorubicin. ClinicalTrials.gov. Retrieved 2012-01-31.
  16. Jump up^ “NCT00101049”. BBR 2778 for Relapsed, Aggressive Non-Hodgkin’s Lymphoma (NHL). ClinicalTrials.gov. Retrieved 2012-01-31.
  17. Jump up^ Vesely N, Eckhardt SG (2010-03-22). “NDA 022-481 PIXUVRI (pixantrone dimaleate) injection” (pdf). Summary Minutes of the Oncologic Drugs Advisory Committee. United States Food and Drug Administration. Retrieved 2012-01-31.
  18. Jump up^ “Cell Therapeutics Formally Appeals FDA’s Nonapprovable Ruling for Pixantrone”. GEN News. 2010-12-03.
  19. Jump up^ “Pixantrone Now Available in Europe on a Named-Patient Basis”. Retrieved 2012-01-31.
  20. Jump up^ Gonsette RE, Dubois B (August 2004). “Pixantrone (BBR2778): a new immunosuppressant in multiple sclerosis with a low cardiotoxicity”. J. Neurol. Sci. 223(1): 81–6. doi:10.1016/j.jns.2004.04.024. PMID 15261566.
  21. Jump up^ Mazzanti B, Biagioli T, Aldinucci A, Cavaletti G, Cavalletti E, Oggioni N, Frigo M, Rota S, Tagliabue E, Ballerini C, Massacesi L, Riccio P, Lolli F (November 2005). “Effects of pixantrone on immune-cell function in the course of acute rat experimental allergic encephalomyelitis”. J. Neuroimmunol. 168 (1-2): 111–7.doi:10.1016/j.jneuroim.2005.07.010. PMID 16120465.
  22. Jump up^ Ubiali F, Nava S, Nessi V, Longhi R, Pezzoni G, Capobianco R, Mantegazza R, Antozzi C, Baggi F (February 2008). “Pixantrone (BBR2778) reduces the severity of experimental autoimmune myasthenia gravis in Lewis rats”. J. Immunol. 180 (4): 2696–703. PMID 18250482.
  23. Jump up^ Colombo R, Carotti A, Catto M, Racchi M, Lanni C, Verga L, Caccialanza G, De Lorenzi E (April 2009). “CE can identify small molecules that selectively target soluble oligomers of amyloid beta protein and display antifibrillogenic activity”. Electrophoresis 30(8): 1418–29. doi:10.1002/elps.200800377. PMID 19306269.


McLean Hospital study finds herbal extract may curb binge drinking – kudzu


Ralph Turchiano's avatarCLINICALNEWS.ORG

18 May 2012

Belmont, MA – An extract of the Chinese herb kudzu dramatically reduces drinking and may be useful in the treatment of alcoholism and curbing binge drinking, according to a new study by McLean Hospital and Harvard Medical School researchers.

“Our study is further evidence that components found in kudzu root can reduce alcohol consumption and do so without adverse side effects,” said David Penetar, PhD, of the Behavioral Psychopharmacology Research Laboratory at McLean Hospital, and the lead author of the study. “Further research is needed, but this botanical medication may lead to additional methods to treat alcohol abuse and dependence.”

In the study, published in the current issue of Drug and Alcohol Dependence, researchers in the Behavioral Psychopharmacology Research Laboratory at McLean Hospital looked at one of the major components of the kudzu root—the isoflavone puerarin—to determine whether it would reduce alcohol consumption in a laboratory simulation…

View original post 389 more words

Component of pizza seasoning herb oregano kills prostate cancer cells – Oregano


Ralph Turchiano's avatarCLINICALNEWS.ORG

04 May2012

San Diego, CA — Oregano, the common pizza and pasta seasoning herb, has long been known to possess a variety of beneficial health effects, but a new study by researchers at Long Island University (LIU) indicates that an ingredient of this spice could potentially be used to treat prostate cancer, the second leading cause of cancer death in American men.

Prostate cancer is a type of cancer that starts in the prostate gland and usually occurs in older men. Recent data shows that about 1 in 36 men will die of prostate cancer. Estimated new cases and deaths from this disease condition in the US in 2012 alone are 241,740 and 28,170, respectively. Current treatment options for patients include surgery, radiation therapy, hormone therapy, chemotherapy, and immune therapy. Unfortunately, these are associated with considerable complications and/or severe side effects.

View original post 329 more words

A CURED CASE OF “OSTEO-ARTHRITIS” BY AYURVEDA TREATMENT ; PATIENT WAS ADVISED FOR KNEE JOINT REPLACEMENT ; “घुटना प्रत्यारोपड़” के लिये एडवाइस किये गये ओस्टियो-आर्थ्राइटिस रोगी का आयुर्वेदिक उपचार से पूर्ण आरोग्य ;


Dr.D.B.Bajpai's avatar**आधुनिक युग आयुर्वेद ** ई०टी०जी० आयुर्वेदास्कैन ** DIGITAL AYURVEDA TRIDOSHO SCANNER**AYURVED H. T. L. WHOLE-BODY SCANNER**आयुषव्यूज रक्त केमिकल केमेस्ट्री परीक्षण अनालाइजर ** डिजिटल हैनीमेनियन होम्योपैथी स्कैनर **

आयुर्वेद चिकित्सा विग्यान मे आर्थ्राराइटिस के रोग का बहुत सटीक और उत्तम किस्म का इलाज सम्भव पहले भी था आदि काल से था और अब आयुर्वेद के परीक्षण पर आधारित तकनीको के अमल मे लाने से यह अधिक सटीक और fool proof  हो गया है /

एक महिला ४७ साल उम्र , जिसको ओस्टियो आर्थ्राइटिस की तकलीफ थी , उसको घूटना प्रत्यारोपड़ KNEE JOINT REPLACEMENT के लिये कहा गया / लेकिन इस महिला के पास पैसा होते हुये भी उसने घुटना प्रत्यारोपड़ नही करवाया , इसका कारण जो भी रहा हो / क्योन्कि उसने जब देखा कि घुटना का प्रत्यारोपड़ किये गये लोगो को किस तरह की हालत होती है उसे देखकर रोगिनी ने knee joint replacement  का इरादा बदल दिया /

किसी ने इस महिला को आयुर्वेद की चिकित्सा कराने के लिये कहा / इस महिला ने यह ढून्ढना शुरू किया कि कौन सा आयुर्वेद का चिकित्सक उसकी सहायता…

View original post 921 more words

Tea polyphenol extracts induce weight loss


ayurvedicteas's avatarAyurvedic Herbal Teas

Tea polyphenol extracts induced weight loss effects and anti-oxidant activity.

Research, via an animal study,  by Heber et al suggests that tea extracts found in Green tea may help with weight loss.  A tea rich diet led to significantly lower body weight, total visceral fat volume and liver lipid weight.

It seems that, as well as reducing overall food intake, the extracts are able to induce certain types of gene expression via biochemical changes in the body.  This could be great news if you are trying to control your weight in a natural way.

Green Tea Black Bacground

View original post